

The use of continuous glucose monitoring (CGM) continues to increase and has become the standard of care for the management of type 1 diabetes and insulin-treated type 2 diabetes, with more research showing benefit in other diabetes populations. When individuals with diabetes and care teams discuss their CGM data, they often focus on time in range (TIR), time below range (TBR), and the glucose management indicator (GMI) to assess overall diabetes management.(1) However, what is often overlooked is how much glucose variability (fluctuations) people with diabetes are experiencing.
Fortunately, the level of glucose variability, defined as the percent coefficient of variation (%CV), is readily available on the Ambulatory Glucose Profile (AGP) Report. (2,3) This article describes what %CV is, how it is calculated, why it is important, and what can be done to lower it.
What is %CV and how is it calculated?
%CV is a measure of variability (or fluctuation) in glucose readings during the CGM reporting period. The higher the %CV, the more variability in glucose compared to the average glucose.
It is calculated by dividing the standard deviation of all glucose values for the CGM reporting period by the CGM-derived average glucose, multiplied by 100, yielding a %CV. The %CV is reported on the AGP Report as part of the Glucose Metrics section.
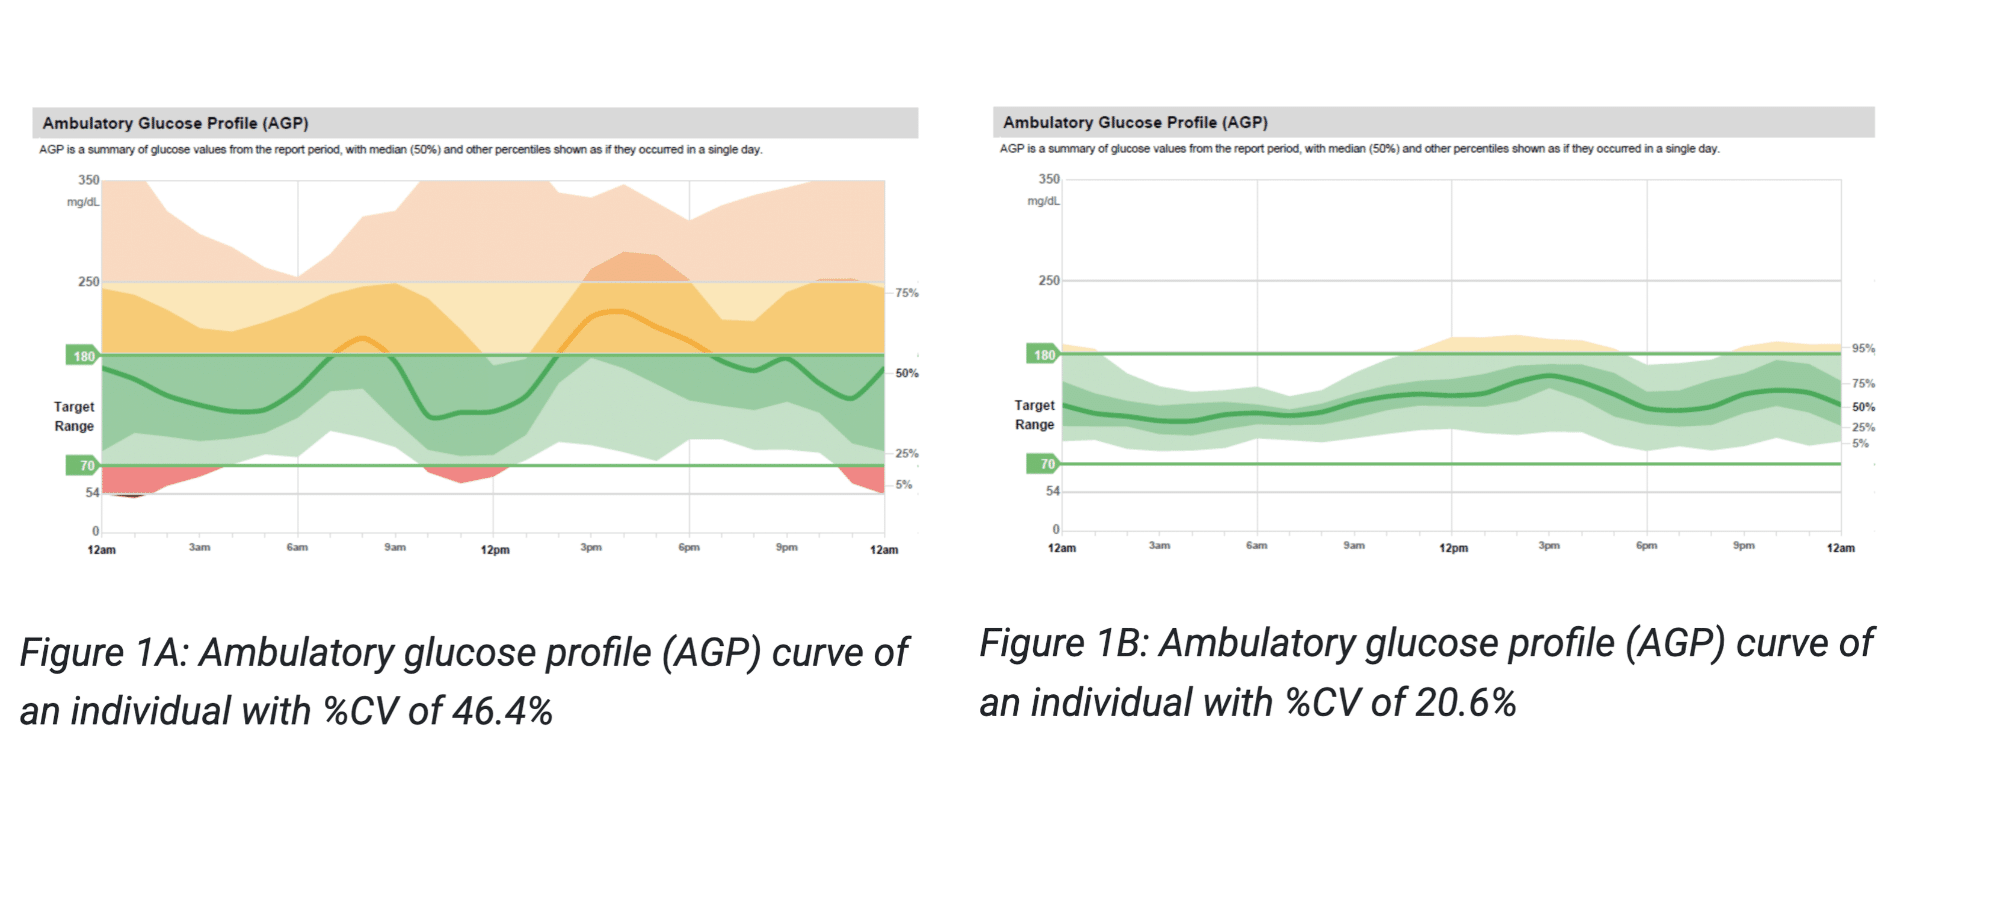
To illustrate the difference between a high and low %CV, compare the AGP curves in Figures 1A and 1B, each representing 14 days of CGM data with %CV of 46.4% and 20.6%, respectively. Figure 1A shows wide fluctuations in glucose throughout the 24-hour period with a large interquartile range (the range of glucose values between the 25th and 75th percentile) compared to Figure 1B with very flat glucose and a narrow interquartile range. The goal is to have an AGP curve closer to Figure 1B that is “flat, narrow and in-range”. (1)
Why is %CV Important
%CV is of clinical importance for several reasons:
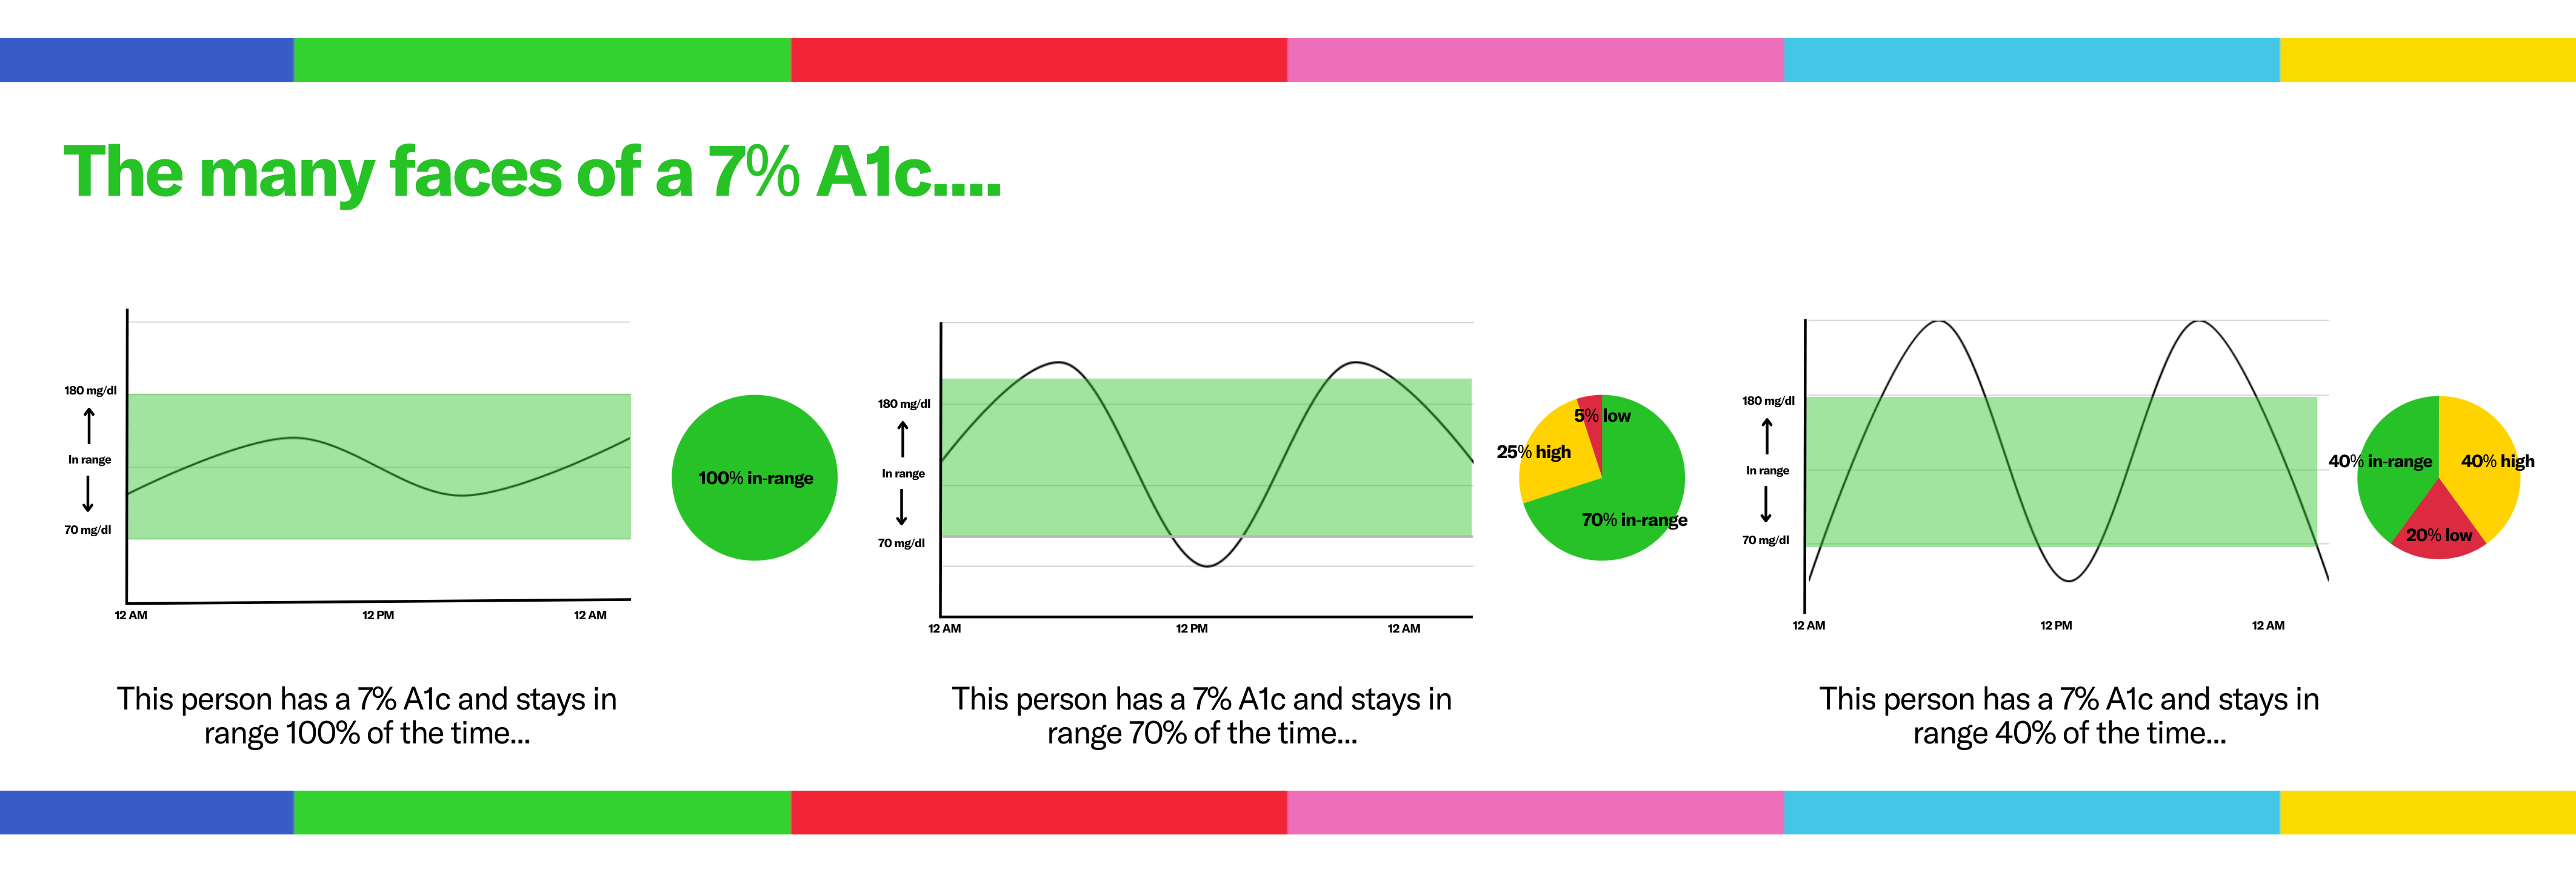
- Two individuals with the same average blood glucose, GMI, or glycated hemoglobin A1c (A1C) may have dramatically different glycemic variability and %CVs (see Figure 2).
- High %CV is a strong predictor of hypoglycemia and TBR. (4-6) There is a low risk of hypoglycemia when the %CV is low (e.g. <20%) and increases exponentially as %CV increases. (7,8)
- High %CV is associated with microvascular complications including retinopathy and neuropathy.(9) Less is known about the association of high %CV and macrovascular complications and cardiovascular disease (CVD). However, higher glycemic variability has been implicated as a new risk factor for CVD because it leads to more oxidative stress, inflammation, and endothelial dysfunction.(10)
What is the Target for %CV
The target for %CV established by an International Consensus Recommendation for TIR is ≤36%. This was established as the risk of hypoglycemia increases significantly above this threshold.3,5 However, this target is not without controversy, and the Consensus for TIR includes studies that indicate a lower %CV target (e.g.,<33%) may provide additional protection against hypoglycemia.(3) A more recent study has shown that to achieve a recommended target of TIR of >70% and TBR of <4%, a %CV of 34% or less is required.(11) Interestingly, this study also showed that it is nearly impossible to achieve a TIR of >70% if the %CV is >50%.
How to Lower %CV
Several articles have described ways to lower glycemic variability and are summarized in the list below.(9,11,12)
Diabetes Technology
- Start using CGM and its metrics to track %CV
- Use CGM trend arrows to reduce hyperglycemia and hypoglycemia
- Consider use of automated insulin delivery system
Lifestyle and Nutrition
- Consider adjusting nutrition goals, with glycemic index in mind
- Introduce or re-educate carbohydrate counting
- Suggest eating vegetables and protein first, followed by carbohydrate
- Include post-meal physical activity (if possible) to reduce glucose rise
- Participate in aerobic exercise and resistance training
Medication
- Take insulin as prescribed (e.g., take mealtime insulin before eating, avoid skipping doses)
- Use fast-acting insulin analogs and longer-acting basal insulins to lower post-meal glucose and flatten overnight glucose, respectively
- Select noninsulin therapies that don’t cause hypoglycemia (e.g., GLP-1 receptor agonist-based therapy, SGLT2 inhibitors)
References
- Martens, T W, Simonson, GD, & Bergenstal, RM. Using continuous glucose monitoring data in daily clinical practice. Cleveland Clinic Journal of Medicine, 2024; 91(10): 611-620.
- Bergenstal RM, Ahmann AJ, Bailey T, et al. Recommendations for Standardizing Glucose Reporting and Analysis to Optimize Clinical Decision Making in Diabetes: The Ambulatory Glucose Profile. Journal of Diabetes Science and Technology. 2013; 7(2):562-578.
- Battelino T, Danne T, Bergenstal RM, et al. Clinical targets for continuous glucose monitoring data interpretation: recommendations from the international consensus on time in range. Diabetes care. 2019; 42(8):1593-603.
- Rama Chandran S, Tay WL, Lye WK, et al. Beyond HbA1c: Comparing Glycemic Variability and Glycemic Indices in Predicting Hypoglycemia in Type 1 and Type 2 Diabetes. Diabetes Technology & Therapeutics. 2018; 20(5):353-362.
- Monnier L, Colette C, Wojtusciszyn A, Dejager S, Renard E, Molinari N, Owens DR. Toward defining the threshold between low and high glucose variability in diabetes. Diabetes care. 2017; 40(7):832-8.
- Ceriello A, Monnier L, Owens D. Glycaemic variability in diabetes: clinical and therapeutic implications. Lancet Diabetes Endocrinol. 2019; 7(3):221-230.
- Rodbard D. Hypo- and Hyperglycemia in Relation to the Mean, Standard Deviation, Coefficient of Variation, and Nature of the Glucose Distribution. Diabetes Technology & Therapeutics. 2012; 14(10):868-876.
- Rodbard D. Glucose time in range, time above range, and time below range depend on mean or median glucose or HbA1c, glucose coefficient of variation, and shape of the glucose distribution. Diabetes technology & therapeutics. 2020; 22(7):492-500.
- Wilmot EG, Choudhary P, Leelarathna L, Baxter M. Glycaemic variability: The under-recognized therapeutic target in type 1 diabetes care. Diabetes Obes Metab. 2019; 21: 2599–2608.
- Belli M, Bellia A, Sergi D, Barone L, Lauro D, Barillà F. Glucose variability: a new risk factor for cardiovascular disease. Acta diabetologica. 2023; 60(10):1291-1299.
- Xu Y, Dunn TC, Bergenstal RM, et al. Time in range, time in tight range, and average glucose relationships are modulated by glycemic variability: Identification of a glucose distribution model connecting glycemic parameters using real-world data. Diabetes Technology & Therapeutics. 2024; 26(7):467-77.
- Zhou Z, Sun B, Huang S, Zhu C, Bian M. Glycemic variability: adverse clinical outcomes and how to improve it?. Cardiovascular diabetology. 2020;19(1):102.